Vesicoureteral Reflux (VUR)
Urine flows backwards from the bladder up to the kidney.
What is Vesicoureteral Reflux (VUR)?
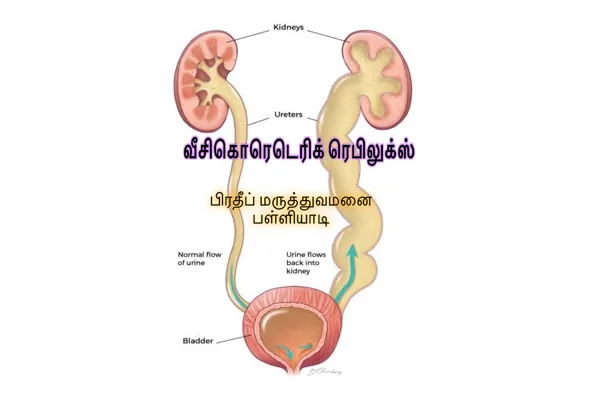
Urine normally travels one way — from the kidney down the ureter into the bladder, and out. In vesicoureteral reflux the valve mechanism where the ureter enters the bladder does not work properly, so when the bladder fills or empties, some urine flows backwards up towards the kidney.
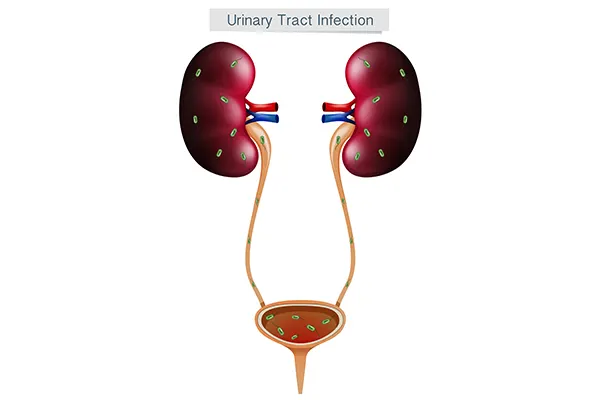
Reflux by itself does not hurt. The danger is infection: infected urine carried up to the kidney can scar it, and scarring over years can affect kidney function and blood pressure.
Reflux is graded from I (mild, urine reaches the ureter only) to V (severe, with a dilated twisted ureter and a swollen kidney). The grade largely decides the treatment.
Many children outgrow mild and moderate reflux as they grow, because the tunnel where the ureter enters the bladder lengthens naturally.
In your language
Vesicoureteral Reflux (VUR)
Urine flows backwards from the bladder up to the kidney.
Urine normally travels one way — from the kidney down the ureter into the bladder, and out. In vesicoureteral reflux the valve mechanism where the ureter enters the bladder does not work properly, so when the bladder fills or empties, some urine flows backwards up towards the kidney.
சிறுநீர் பின்னோக்கி ஏறுதல் (VUR)
சிறுநீர் சிறுநீரகத்திலிருந்து சிறுநீர்ப்பையை நோக்கி ஒரு திசையில் மட்டுமே செல்ல வேண்டும். VUR நிலையில் அது பின்னோக்கி சிறுநீரகத்தை நோக்கி ஏறும். இதனால் அடிக்கடி சிறுநீர் தொற்று ஏற்பட்டு சிறுநீரகம் பாதிக்கப்படலாம். MCUG எனும் பரிசோதனை மூலம் இது உறுதி செய்யப்படுகிறது. பெரும்பாலான குழந்தைகள் வளர வளர இது தானாகவே சரியாகும்; அதுவரை தொற்று வராமல் காப்பதே சிகிச்சை. கடுமையான நிலைகளில் மட்டுமே அறுவை சிகிச்சை தேவை. குழந்தைக்கு காரணமின்றி காய்ச்சல் திரும்பத் திரும்ப வந்தால் சிறுநீர் பரிசோதனை செய்யுங்கள்.
മൂത്രം തിരികെ കയറുന്ന അവസ്ഥ (VUR)
മൂത്രം വൃക്കയിൽ നിന്ന് മൂത്രസഞ്ചിയിലേക്ക് ഒരു ദിശയിൽ മാത്രമേ പോകാവൂ. VUR-ൽ അത് തിരികെ വൃക്കയിലേക്ക് കയറും. ഇത് ആവർത്തിച്ചുള്ള മൂത്രാശയ അണുബാധയ്ക്കും വൃക്കയ്ക്ക് ക്ഷതത്തിനും കാരണമാകാം. MCUG എന്ന പരിശോധനയിലൂടെയാണ് ഇത് സ്ഥിരീകരിക്കുന്നത്. മിക്ക കുട്ടികളിലും വളരുന്നതിനനുസരിച്ച് ഇത് സ്വയം മാറും; അതുവരെ അണുബാധ വരാതെ നോക്കുകയാണ് ചികിത്സ. ഗുരുതരമായ ഘട്ടങ്ങളിൽ മാത്രമേ ശസ്ത്രക്രിയ വേണ്ടിവരൂ. കാരണമില്ലാതെ ആവർത്തിച്ച് പനി വന്നാൽ മൂത്രപരിശോധന നടത്തുക.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Repeated urinary tract infections — often the only sign
- Unexplained fever in a baby or young child with no other obvious cause
- Pain or burning while passing urine, or pain in the side or tummy
- Foul-smelling or cloudy urine
- Poor weight gain or feeding in a baby
- Bedwetting or new daytime wetting in a child who was previously dry
- Sometimes no symptoms at all — found on scans after a swollen kidney was seen before birth
How It Is Confirmed
- Urine culture to confirm and identify infection
- Ultrasound of the kidneys and bladder as the first imaging test
- MCUG (micturating cystourethrogram) — the test that actually shows and grades reflux, done by filling the bladder through a fine catheter and taking X-ray pictures while the child passes urine
- DMSA scan to check whether the kidney has already been scarred and how well each kidney is working
- Blood pressure and kidney function tests where scarring is present
How It Is Treated
- Most children are managed without surgery. The aim is to keep the urine free of infection while the child grows out of the reflux.
- Low-dose preventive antibiotics at night are commonly used in babies and in higher grades of reflux.
- Treating constipation and bladder-emptying habits matters more than parents expect — a full rectum and a poorly emptying bladder both worsen reflux and infection.
- Endoscopic injection: a bulking agent is injected at the ureter opening through a cystoscope to strengthen the valve. A short day-care procedure with no external cut.
- Ureteric reimplantation: an operation that re-tunnels the ureter into the bladder wall to create a working valve. This is the definitive repair for high-grade or failed cases.
- Regular follow-up with ultrasound and urine checks continues either way.
Does My Child Need Surgery?
Not every child with Vesicoureteral Reflux (VUR) needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Breakthrough urinary infections keep occurring despite preventive antibiotics
High-grade reflux (grade IV or V), which is much less likely to resolve on its own
New or progressive kidney scarring on DMSA, or falling kidney function
Reflux persisting into later childhood with no sign of improvement
The family cannot reliably continue long-term antibiotics and surveillance
What Happens Over Time
Most children outgrow mild and moderate reflux, and with infections kept away the kidneys stay healthy. Where scarring has already happened it is permanent, but kidneys have a large reserve and most children with limited scarring grow up with normal function, normal blood pressure and no restrictions.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
The reflux itself cannot be prevented. Kidney damage very often can be — by treating urinary infections promptly, keeping the bowels regular, and not skipping the follow-up scans.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Endoscopic injection is usually day care. Ureteric reimplantation typically means 3 to 5 days in hospital.
Recovery at home
After open reimplantation there may be bladder spasms and blood-stained urine for a few days, which settle. Normal activity in 2 to 3 weeks.
Follow-up
Ultrasound and urine checks after the procedure, then continued surveillance — kidney protection is a long-term job, not a one-visit fix.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Vesicoureteral Reflux (VUR), not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions


Reflux is about protecting the kidneys, not just treating each infection.
Most children grow out of it without surgery, but only if the urine is kept clear and the kidneys are watched while they do. Bring the scan and culture reports and we will set out the plan.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.