Intussusception
One part of the bowel slides into the next — an emergency.
What is Intussusception?
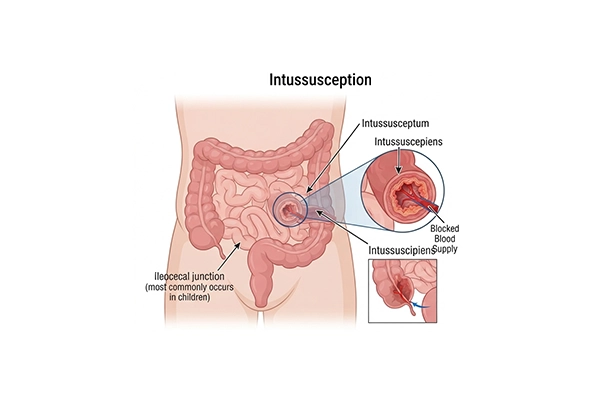
Intussusception happens when one segment of bowel telescopes into the segment next to it, like the sections of a collapsible telescope. The trapped bowel swells, its blood supply is squeezed, and the bowel becomes obstructed.
It is most common between about 3 months and 3 years of age, with a peak around 6 to 9 months, and it often follows a viral illness.
This is a time-critical emergency. Treated within hours it can usually be resolved without an operation. Left for a day or two the bowel can die, and surgery to remove it becomes necessary.
The classic sign is a previously well baby who suddenly draws up the legs and screams in episodes, then falls limp and pale between them.
In your language
Intussusception
One part of the bowel slides into the next — an emergency.
Intussusception happens when one segment of bowel telescopes into the segment next to it, like the sections of a collapsible telescope. The trapped bowel swells, its blood supply is squeezed, and the bowel becomes obstructed.
குடல் ஒன்றுக்குள் ஒன்று நுழைதல்
குடலின் ஒரு பகுதி அடுத்த பகுதிக்குள் நுழைந்து அடைப்பை ஏற்படுத்தும் நிலை இது. 3 மாதம் முதல் 3 வயது வரையிலான குழந்தைகளில் அதிகம். திடீரென கால்களை வயிற்றோடு இழுத்து கடுமையாக அழுதல், இடையில் சோர்வாகவும் வெளிறியும் கிடத்தல், பச்சை நிற வாந்தி, ரத்தம் கலந்த சளி போன்ற மலம் — இவை அறிகுறிகள். இது மணிநேரங்களில் சிகிச்சை தேவைப்படும் அவசர நிலை. சீக்கிரம் வந்தால் அறுவை சிகிச்சை இல்லாமலே காற்று அல்லது திரவம் மூலம் சரிசெய்யலாம். தாமதித்தால் குடலை அகற்ற வேண்டியிருக்கும். காத்திருக்க வேண்டாம்.
കുടൽ ഒന്നിനുള്ളിൽ ഒന്ന് കയറുന്ന അവസ്ഥ
കുടലിന്റെ ഒരു ഭാഗം അടുത്ത ഭാഗത്തിനുള്ളിലേക്ക് കയറി തടസ്സമുണ്ടാക്കുന്ന അവസ്ഥയാണിത്. 3 മാസം മുതൽ 3 വയസ്സു വരെയുള്ള കുട്ടികളിലാണ് കൂടുതൽ. പെട്ടെന്ന് കാലുകൾ വയറ്റിലേക്ക് വലിച്ച് ഉറക്കെ കരയുക, ഇടയ്ക്ക് തളർന്ന് വിളറി കിടക്കുക, പച്ച ഛർദ്ദി, രക്തം കലർന്ന കഫം പോലുള്ള മലം — ഇവയാണ് ലക്ഷണങ്ങൾ. മണിക്കൂറുകൾക്കുള്ളിൽ ചികിത്സ വേണ്ട അടിയന്തരാവസ്ഥയാണ്. നേരത്തെ എത്തിയാൽ ശസ്ത്രക്രിയ കൂടാതെ വായു ഉപയോഗിച്ച് ശരിയാക്കാം. വൈകിയാൽ കുടൽ നീക്കം ചെയ്യേണ്ടിവരും.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Sudden episodes of severe crying with the legs drawn up, lasting a few minutes, then settling
- Between episodes the baby is unusually quiet, pale, floppy or sleepy — this lethargy is an important sign
- Vomiting, which becomes green (bile-stained) as the obstruction progresses
- Refusing feeds
- Stool mixed with blood and mucus, described as looking like red-currant jelly — a late sign, so do not wait for it
- A sausage-shaped lump felt in the tummy
- A swollen tummy and a very unwell child if treatment is delayed
How It Is Confirmed
- Ultrasound of the abdomen — reliable, quick and the test of choice, showing the characteristic target appearance
- Clinical assessment of hydration and how unwell the child is, which drives the urgency
- X-ray of the abdomen where obstruction or perforation is suspected
- Blood tests before any procedure
How It Is Treated
- Resuscitation first: an intravenous line, fluids, and a tube to empty the stomach.
- Non-operative reduction is the first-line treatment in a stable child — air or fluid is introduced into the bowel under image guidance to push the telescoped segment back. It succeeds in most children treated early.
- Surgery is needed if reduction fails, if the child is too unwell for it, or if there are signs of perforation. At operation the bowel is reduced manually, and any dead segment is removed.
- Antibiotics and supportive care around the procedure.
- Intussusception can recur, most often within the first 48 hours, so the child is observed after successful reduction.
Does My Child Need Surgery?
Not every child with Intussusception needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Non-operative reduction has failed or is incomplete
The child has signs of peritonitis or perforation, or is too unstable for reduction
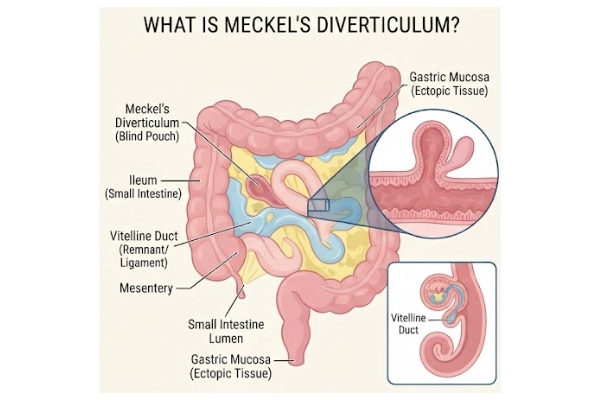
A lead point such as a Meckel’s diverticulum, polyp or duplication cyst is present — more likely in children over 3 years
Repeated recurrences, which prompt a search for an underlying cause
What Happens Over Time
Very good when treated within hours, and most children are reduced without an operation and home in a day or two. Delay is what changes the outlook, because bowel that has lost its blood supply has to be removed. Recurrence happens in a small number, usually within the first two days.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
It cannot generally be prevented. Recognising the pattern early — screaming episodes with unusual limpness in between — is what prevents harm.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
After successful non-operative reduction, usually 1 to 2 days of observation. After surgery, typically 5 to 7 days.
Recovery at home
Feeding restarts once the bowel is working. Recovery after non-operative reduction is quick; after bowel resection it takes longer.
Follow-up
A review after discharge, and clear written advice on the signs of recurrence, which parents must know before going home.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Intussusception, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions
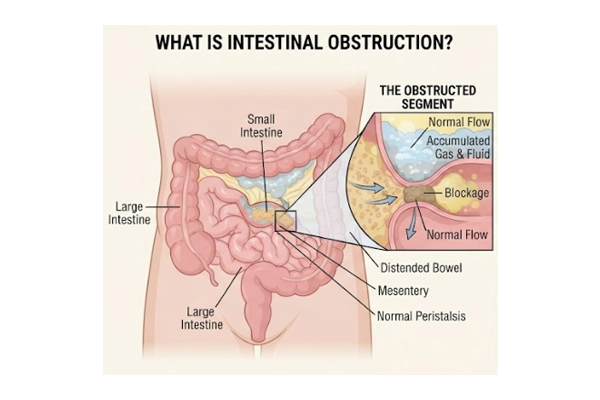
This is an emergency, and hours change the treatment.
A baby with attacks of screaming, drawing up the legs and redcurrant-jelly stool needs to be seen now. Treated early it is often pushed back without an operation at all.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.